



 nova página do texto(beta)
 Inglês (pdf)
 Artigo em XML
 Referências do artigo

 Tradução automática
 Enviar este artigo por email
 Citado por SciELO
 Similares em
SciELO

 Permalink

Introduction
Primary pleural liposarcoma (PPL) is an extremely rare malignant tumor, originating from mesenchymal cell remnants and very rarely from a pre-existing lipoma. A total of 43 cases have been reported in the literature worldwide, with the first case report being published by Ackerman and Wheeler in 1942. In the documented cases, it predominates in the male gender, being more frequent in the 5th decade of life (Table 1). The diagnosis should be suspected on images containing fat density with or without calcifications by chest computed tomography (CT) and confirmed by histopathological study. Surgical resection of the tumor is the therapeutic method of choice, although with risks of recurrence at 5 years1.
Table 1 Global amount of pleural liposarcoma found since 1942, with a total of 43 cases reported until 2023
| Author (year) | Age/sex | Pleura site | Tumor size (cm) | Histology | Therapy | Follow-up (months) |
|---|---|---|---|---|---|---|
| Ackerman and Wheeler (1942) | 50/F | Left | Nt | Nt | Autopsy | FE/12 M |
| Gupta and Paolini (19767) | 51/M | Right | 21 | POR | Autopsy | DN |
| Ambrosio (1974) | 52/M | Left | Nt | Nt | C-Res | VSEE/66 |
| Wouters et al. (1983) | 19/F | Left | 3.5 | MYX | C-Res + Rad | Alive/55 |
| Evans (1985) | 61/M | Left | Nt | MYX | Autopsy | FE |
| Evans et al. (1987) | 45/M | Left | Nt | MYX | Autopsy | MOE/0.07 |
| Gregor et al. (1987) | 54/M | Right | 2-2.25 | LPBD | C-Res | MCD/108 |
| Munk and Muller (1988) | 27/F | Left | Nt | Nt | Nt | DN |
| Carroll et al. (1992) | 23/F | Left | 29-21 | MIXED | C-Res + RT | VSEE/16 |
| Wong et al. (1994) | 38/M | Right | Nt | MY | C-Res + RT | VSEE/5 |
| Batouk (1995) | 55/F | Right | 10 × 7 and 1.5 × 0.5 | LPBD | C-Res | VSEE/16 |
| Okby and Travis (2000) | 45/F | DN | 16 | MYX/RO | P/I-Res + QT | FE/7 |
| Okby and Travis (2000) | 73/M | Right | Nt | MYX | P/I-Res | FE/9 |
| Okby and Travis (2000) | 67/M | Right | 18.5 | LPBD | Nt | MCD/16 |
| Okby and Travis (2000) | 80/M | Right | 20 | MYX | C-or/I-Res | DN |
| Tosson and Krismann (2000) | 51/M | 2 Right/ 1 recurrent: left | 18 × 12 × 7 | MYX | C-Res/RAD | VSEE/5Y |
| Minniti et al. (2005) | 50/M | Left | 13 | WDL | C-Res + Rad | VSEE/12 |
| Takanami and Imamura (2005) | 59/M | Right | 12-5.3 | LPD | C-Res | VSEE/6 |
| Goldsmith and Papaguiamnopoulos (2007) | 42/M | Left | Nt | MYX | C-Res + Rad | Alive/12 |
| Papaguiamnopoulos and Goldsmith (2007) | 80/F | Left | Nt | MYX | P/I-Res | FE/8 |
| Benchetritt et al. (2007) | 76/F | Left | 18-11 | LPD | C- o P/I-Res | MOE/0.1 |
| Peng et al. (2007) | 56/F | Left | Nt | LPBD | C-Res | VSEE/18 |
| Dagli (2008) | 56/F | Left | Nt | MYX | ND | DN |
| Alloubi et al. (2008) | 58/M | Left | Nt | MYX | C-Res + Rad | VSEE/10 |
| Elsayed (2010) | 47/M | Right | 18 × 12 × 10 | LPBD | C-Res | VSEE |
| Chen et al. (2014) | 19/M | DN | Nt | LPBD | C-Res | Alive/56 |
| Chen et al. (2014) | 30/F | DN | Nt | LPBD | C-Res | VSEE/48 |
| Chen et al. (2014) | 60/M | DN | Nt | LPBD | C-Res | VSEE/43 |
| Chen et al. (2014) | 20/F | DN | Nt | MYX | C-Res | Alive/90 |
| Chen et al. (2014) | 54/M | DN | Nt | MYX | C-Res | VSEE/26 |
| Chen et al. (2014) | 41/M | DN | Nt | LPD | C-Res | Died/15 |
| Chen et al. (2014) | 53/M | DN | Nt | LPD | C-Res | Died/11 |
| Chen et al. (2014) | 61/M | DN | Nt | LPBD | P/I-Res | VSEE/18 |
| Chen et al. (2014) | DN/F | DN | DN | DN | DN | DN |
| Carrillo (2014) | 49/F | Left | 19×10 | PL | C-Res | DN |
| Albujar Ching (2016) | 56/M | Right | 2 kg | MYX | C-Res | DN |
| Wang et al. (2017) | 43/F | Left | 21 | MYX | C-Res | VSEE/8 |
| Matsukumu (2018) | 45/M | Left | 10 | LPD | P/I-Res | FE/4.2 |
| Prabhakar (2019) | 32/M | Right | 20.8 × 13.6 | MYX | QT-RT | VSEE |
| Kang (2020) | 66/M | Left | 4.5 × 3.3 × 3 | C-Res | C-Res | VSEE |
| Layek (2022) | 22/M | Left | 23 × 18 | DN | DN | VSEE |
| Palacios (2022) | 46/M | Right | 20 × 25 | MYX | I-Res + QT | Alive |
F: female; M: male; VSEE: alive with no evidence of disease; EF: died of disease; EOM: died of another disease; MCD: died of unknown causes; QT: chemotherapy; C-Res: complete resection; RT: radiotherapy; Nt: not size; P/Res: palliative and incomplete resection; By: poorly differentiated; Myx: myxoid; LPBD: well-differentiated liposarcoma; MYX/RO: myxoid and rounded type; LPD: dedifferentiated liposarcoma; PL: pleomorphic; DN: data not available.
Clinical case
A 61-year-old male presented with a history of systemic arterial hypertension of 25 years. Her condition began 2 months before hospitalization with asthenia, adynamia, non-productive cough, distal cyanosis, and rapidly progressive dyspnea. Physical examination included condensation syndrome in the left hemithorax. Laboratory studies Hb: 19, platelets: 118, leukocytes: 5.9, Dimer D: 4561. CT scan of the chest with image of hypodense tumor in the left hemithorax with Hounsfield units of −30 to 130 fatty tissue range and dimensions 29.5 × 16.1 × 21.9 cm, observing ovoid lesions with hyperdense walls with the presence of calcifications and hypodense centers near the posterior aspect of the hemithorax. Transthoracic biopsy was taken with an Abrams needle, obtaining samples of pearly tissue, histological sections identify neoplastic lesion composed of adipose tissue, with a solid growth pattern. Immunolabeling for MDM2 was performed, which was negative. During his hospital stay, the patient presented respiratory and hemodynamic deterioration and was admitted to the intensive care unit, where he later died due to complications secondary to the underlying diagnosis.
In the autopsy study, significant congestion was observed in the cephalic and cervical segments, jugular engorgement, and subclavian veins, with data of a superior vena cava syndrome. At the opening of the thoracic cavity, a tumor measuring 30 × 20 × 15 cm, well defined, with a lobed surface and adipose appearance, was observed in an anterior situation and occupying the entire left hemithorax (Fig. 1A). With collapse of the ipsilateral lung, displacement of the heart and mediastinal structures toward the right hemithorax (Fig. 1B). The appearance of the tumor was homogeneous with an adipose appearance, light yellow in color, with foci of necrosis and calcifications. Histologically, the tumor was composed of neoplastic adipocytes of mature appearance, with variation in their shape and size, accompanied by a fine vascular network with a characteristic chicken wire appearance (Fig. 1C). Nuclear atypia was demonstrated in both neoplastic adipocytes and stromal cells (Fig. 1D). Foci of sclerosis were observed, with dystrophic calcification, no evidence of dedifferentiation or heterologous elements was found. With the above, the diagnosis of well-differentiated liposarcoma, adipocytic subtype, was concluded. Immunohistochemical reactions were performed as a diagnostic adjunct, demonstrating diffuse cytoplasmic and nuclear positivity for S100 (Fig. 1E), and focal nuclear positivity for p16 in neoplastic adipocytes (Fig. 1F), as well as positivity for CD34 in blood vessels. Immunoreactions were performed for MDM2 and CDK4, which were negative; although it is expected to find positive these last markers since these oncogenes are molecularly amplified, their negativity does not rule out the diagnosis. In addition to what has already been mentioned, two previously unidentified lesions were found in the thyroid gland. A classic variant papillary thyroid carcinoma located in the left thyroid lobe, which measured 1.2 × 1.0 × 1.0 cm, and a clear cell follicular adenoma, located in the upper portion of the isthmus, which measured 1.5 × 1.3 × 1.2 cm.
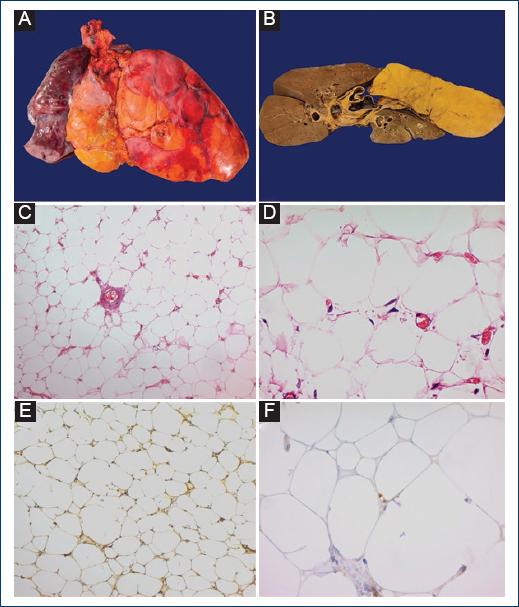
Figure 1 Liposarcoma. A: fresh cardiopulmonary block. B: tomographic section, piece fixed in formaldehyde. C: variation in cell size, vasculature in chicken wire, H&E, ×10. D: adipocytes with nuclear atypia, H&E, ×40. Immunoreactions: E: S100, positive in nucleus and cytoplasm of neoplastic adipocytes, ×10. F: p16 focal nuclear positive in neoplastic adipocytes, ×40.
Discussion
PPL is a rare tumor, accounting for 10% of tumors at the pleural level, other pleural lesions include benign lipomas, hemangioendotheliomas, hemangiopericytomas, angiomas, localized fibrous tumor of the pleura, and non-neoplastic cysts. PPL is usually slow-growing with an expansive rather than an infiltrative behavior, with non-specific clinical manifestations, leading to a delay in its diagnosis2-4.
The World Health Organization classified this tumor into well-differentiated liposarcomas (40-50%), myxoid (20-30%), dedifferentiated subtype (15-20%), and pleomorphic (5-10%), depending on the histological components of the tumor. It occurs in adults in the fourth or fifth decade of life without gender predominance. Myxoid liposarcoma shows a specific and reciprocal chromosomal translocation that occurs in more than 95% of t(12; 16), (q13:p1), fusing the CHOP and FUS genes, causing a dysregulation in adipocyte differentiation and allowing the proliferation of immature forms. The round cell variant is characteristic and known for its worse prognosis5. Liposarcoma is thought to be derived from residual remnants of primitive mesenchymal tissue that may undergo a conformational change to malignant tissue, which later develops as a pleural liposarcoma6,7.
In imaging studies it is described as a well-defined extrapulmonary mass that may have the presence of calcifications that can cause displacement of thoracic structures8. Color Doppler ultrasound can be useful in depicting the solid nature of these tumors and assessing the internal vascularity of the tumor. MRI is the study of choice for defining soft tissue tumors, delineating their location and planning the surgical procedure9. Atypical lipomatous tumor/well-differentiated liposarcoma, myxoid/round cell liposarcoma are S-100 protein positive and variably MDM2 positive. Pleomorphic liposarcoma is variably positive for both S-100 protein and MDM2, and well-differentiated liposarcoma is generally only positive for vimentin5,10.
There are studies that suggest that p16 has greater sensitivity and specificity for the detection of well-differentiated liposarcoma and dedifferentiated liposarcoma; however, its diagnostic yield is higher in combination with MDM2 and CDK4. Although molecular confirmation of this tumor is desirable by demonstrating the amplification of MDM2 and/or CDK4, the morphological study and the clinical context of the tumor make the diagnosis. The treatment of choice is wide and complete resection, provided that adjacent structures allow it. Surgery is complemented by adjuvant radiation therapy, which has been shown to improve local control and survival rate, and sometimes with chemotherapy with doxorubicin, dacarbazine, and ifosfamide. Tumor recurrence is predominantly in the affected hemithorax; however, it can occur in the contralateral hemithorax and is in 70-90% of cases, with a 5-year survival of 71%9,11,12.
Conclusion
Pleural liposarcoma is a rare tumor worldwide, the diagnosis is usually made late due to the presence of non-specific symptoms, being important to note that this entity should be suspected when a tumor with the presence of fat density in the thoracic cavity is found. However, there are no specific lesions, so the gold standard continues to be the histopathological study.

