



 nueva página del texto (beta)
 Inglés (pdf)
 Artículo en XML
 Referencias del artículo

 Traducción automática
 Enviar artículo por email
 Citado por SciELO
 Similares en
SciELO

 Permalink

Introduction
The term "preterm delivery" (PTD) is used to describe a birth that occurs before the 37th week of gestation. One of the most significant contributors to perinatal morbidity and mortality is preterm labor and the subsequent complications that arise from it1. Four primary etiological factors have been identified as contributing to the pathogenesis of PTD: maternal or fetal hypothalamic-pituitary-adrenal activation, infection, decidual hemorrhage, and pathologic uterine distension2.
As defined by the American College of Obstetricians and Gynecologists, cervical insufficiency (CI) is characterized by cervical dilatation that occurs in the second trimester without concurrent uterine contractions and membrane rupture3,4. CI is an important cause of PTD, accounting for 1% of all pregnancies and 8% of recurrent second-trimester losses5.
The diagnosis of CI is based on obstetric history or measurement of cervical length (CL) by transvaginal ultrasonography (TVU). It is important to prolong the gestation period in pregnant patients diagnosed with CI3. CL screening is a reliable method for identifying patients at risk of spontaneous PTD. A CL value of 25 mm or less, as determined by TVU in the second trimester of pregnancy, is indicative of a short cervix6.
There are two principal treatment modalities for CI: surgical and conservative. The conservative treatment approach involves a wait-and-see approach, the administration of progesterone, and the use of a pessary. In surgical treatment, the cerclage procedure may be performed either transvaginally or transdominally7. The recent introduction of perioperative therapies has considerably enhanced the safety and efficacy of emergency cervical cerclage. Moreover, evidence indicates that emergency and prophylactic cervical cerclage are similarly effective when antibiotics and tocolytics are used in an appropriate manner8.
At present, there is a paucity of evidence-based guidelines that can definitively determine whether conservative treatment or cervical cerclage is more effective for patients with CI. Consequently, the absence of standardized guidelines and sufficient evidence-based medical evidence results in physicians diagnosing and treating patients based on their personal experience. This can result in not only inconsistent procedures but also the administration of an excessive degree of uniformity in treatment or the delay of the most appropriate treatment option9. In twin pregnancies with a cervix length of < 15 mm or a dilated cervix of > 10 mm, the use of cerclage has been demonstrated to be an effective method for reducing the incidence of PTD and prolonging the gestational period10.
Although there is more information about cerclage in singleton pregnancies, the efficacy of cerclage in multiple pregnancies is still unclear. Therefore, in this study, we aimed to evaluate the perioperative management, maternal, antenatal, and neonatal outcomes of singleton and twin pregnancies undergoing emergency cervical cerclage in the second trimester in a tertiary center. We also investigated the effect of indications for emergency cerclage on obstetric outcomes.
Methods
This study was conducted in the Department of Obstetrics and Gynecology, Faculty of Medicine, Selcuk University, between March 1, 2023, and June 30, 2024. The study was designed in accordance with the principles set forth in the Declaration of Helsinki and received approval from the Selcuk University, Faculty of Medicine Local Ethics Committee (Ethics Committee number: 2023/162) before its commencement. The data pertaining to patients who underwent follow-up and treatment at our clinic were obtained prospectively.
A total of 49 patients who underwent emergency cerclage for cervical shortness or cervical dilatation and whose treatment and delivery took place in our hospital were included in the study. CL was measured using a Voluson E6 (GE Medical Systems, Milwaukee) transvaginal probe with an empty bladder without compression of the anterior cervix, with the image covering at least 50% of the screen. A sagittal section was taken, and the distance between the internal and external os was measured linearly with equal thickness of the anterior and posterior lips of the cervix. The study population consisted of all pregnant women with a TVU-measured CL of < 15 mm between 16 and 27 weeks of gestation or a USG-measured cervical opening of < 4 cm who underwent emergency cervical cerclage. The flow chart for patient selection is given below (Fig. 1).
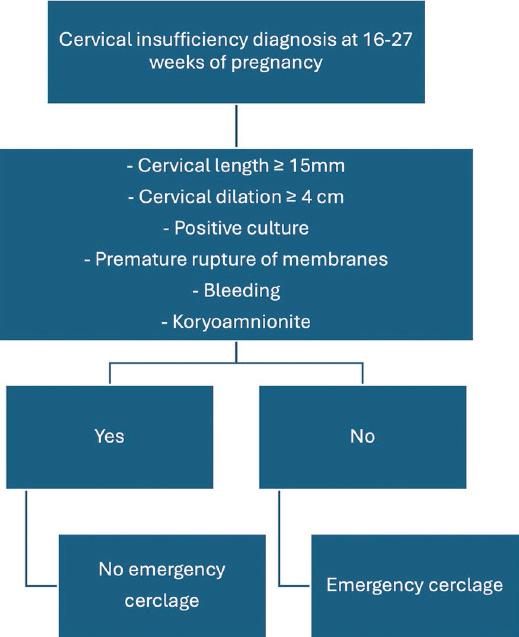
Patients who were diagnosed with CI between 16 and 27 gestational weeks and underwent emergency cerclage were included in the study. In addition, absence of vaginal bleeding, negative active labor contractions, absence of rupture of membranes, negative vaginal and urine cultures, absence of clinical or laboratory findings of chorioamnionitis, and CL < 15 mm were accepted as inclusion criteria in this group. In contrast, exclusion criteria were vaginal bleeding, onset of active labor contractions, CL more than 15 mm or cervical opening more than 4 cm, premature rupture of membranes, culture positivity, or clinical or laboratory positivity.
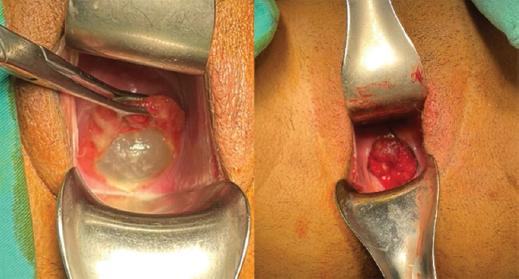
Transvaginal cerclage was performed by experienced specialists (G.O. and A.P.) under spinal anesthesia or sedoanalgesia in the inverted trendelenburg position using an allis clamp in cases with prolapsed membranes and pushing it slightly upward with gauze. In the procedure, cerclage was performed using the McDonald technique using a Mersilene tape suture. The cervical image of a 24w3d pregnant patient with CI before and after cervical cerclage is given in figure. 2.
The patients were initially hospitalized upon the diagnosis of cervical shortness. The results of the vaginal and urine cultures were negative before the performance of the procedure. Intravenous antibiotics and prophylactic indomethacin were initiated during the course of hospitalization. A combination of ceftriaxone (1 g every 24 h), clarithromycin (500 mg every 12 h), and metronidazole (500 mg every 8 h) was employed as the antibiotic regimen. As reported in the study by Oh et al.11 Cervical cerclage was determined to be the optimal course of action following a comprehensive evaluation of the clinical and laboratory results over a minimum of 48 h, particularly in patients exhibiting indications of inflammation on ultrasound (enhanced echogenicity of sludge and amniotic membrane, dense particles in amniotic fluid).
All pregnancy follow-ups after the procedure until delivery were performed by the maternal fetal medicine unit. Progesterone treatment was added to all cases after the cerclage procedure. Progesterone 200 mg every 24 h intravaginally was recommended until 36 weeks of gestation. The cerclage suture was removed at 37 weeks of gestation. The mode of delivery was decided according to obstetric indications.
A comparative analysis was conducted on clinical follow-up, laboratory parameters, pregnancy outcomes, the interval between cerclage and delivery, and neonatal outcomes in singleton and twin pregnancies across the two groups. Furthermore, the obstetric and perinatal outcomes of patients who underwent cerclage for the indications of cervical patency or shortness were also compared between the two groups.
Statistics
The analyses were evaluated using the Statistical Package for Social Sciences (SPSS) 22 package program (SPSS, Inc., Chicago, IL). Descriptive data were presented as absolute and relative frequencies for categorical variables and as means ± standard deviations for continuous variables. A χ2 analysis (Pearson χ2) was employed to ascertain the significance of the observed differences in categorical variables between the groups. The compliance of continuous variables with a normal distribution was evaluated using the Kolmogorov-Smirnov test. A Student's t-test was employed to facilitate a comparison between groups. The level of statistical significance was accepted as p < 0.05 in the analyses.
Results
A total of 49 patients were included in the study. As indicated by the criteria for cerclage application, (n = 18, 37%) were deemed eligible based on ultrasound findings, whereas (n = 31, 63%) met the criteria based on clinical assessment. The results of the comparison of demographic and obstetric characteristics between the two groups are presented in table 1. While cerclage education was more prevalent in singleton pregnancies, USG indication was more common in twin pregnancies. The mean time to delivery was 13.6 ± 4.0 weeks in patients who underwent cerclage according to USG indication and 11.4 ± 4.9 weeks in the group who underwent cerclage according to clinical indication (p = 0.095). The incidence of preterm premature rupture of membranes (PPROM) was 25.8% in the cerclage group with clinical indication and 11.1% in the group with USG indication (p = 0.278).
Table 1 Comparison of demographic and obstetric characteristics of groups based on indication
| Data | Indication for USG (n = 18) Mean ± SD | Clinical indication (n = 31) Mean ± SD | p* |
|---|---|---|---|
| Age | 27.4 ± 4.5 | 28.3 ± 5.9 | 0.559 |
| Gravida | 1.9 ± 0.9 | 2.0 ± 1.4 | 0.092 |
| Parity | 0.2 ± 0.5 | 0.5 ± 1.0 | 0.131 |
| Abortus | 0.2 ± 0.4 | 0.4 ± 1.0 | 0.194 |
| Cerclage week | 21.6 ± 3.0 | 22.2 ± 2.2 | 0.509 |
| Birth week | 35.4 ± 3.3 | 33.4 ± 5.0 | 0.095 |
| Elapsed time (week) | 13.6 ± 4.0 | 11.4 ± 4.9 | 0.090 |
| Number of fetuses (n) | |||
| Singleton (%) | 10 (55.5) | 26 (83.9) | 0.049** |
| Twin (%) | 8 (44.5) | 5 (16.1) | |
| PPROM | |||
| Yes (%) | 2 (11.1) | 8 (25.8) | 0.278** |
| No (%) | 16 (88.9) | 23 (74.2) | |
| Cerclage EFW mean (g) | 395.3 ± 154.7 | 498.1 ± 197.9 | 0.095 |
| Birth EFW mean (g) | 2476.1 ± 711.1 | 2235.4 ± 809.8 | 0.222 |
*Students t-test.
**Χ2 analysis.
PPROM: premature preterm early rupture of membrane; SD: standard deviation, EFW: estimated fetal weight, g: gram.
A comparison was also conducted between the data of patients included in the study with regard to singleton and twin pregnancies. Of the patients included in the study, 13 were identified as having twin pregnancies, representing 27% of the total sample, whereas 36 were identified as having singleton pregnancies, representing 73% of the total sample. The demographic and obstetric data of the groups are presented in table 2. The mean time to delivery was 12.4 ± 5.2 weeks in singleton pregnancies and 12.0 ± 2.9 weeks in twin pregnancies (p = 0.762). The incidence of PPROM-related complications was 19.4% in singleton pregnancies and 23.1% in twin pregnancies (p = 0.781).
Table 2 Comparison of groups based on the number of fetuses of the patients
| Data | Singleton pregnancy (n = 36) Mean ± SD | Twin pregnancy (n = 13) Mean ± SD | p* |
|---|---|---|---|
| Age | 28.2 ± 5.7 | 27.2 ± 4.2 | 0.544 |
| Gravida | 1.9 ± 1.4 | 1.2 ± 0.4 | 0.008 |
| Parity | 0.5 ± 1.0 | 0.0 ± 0.0 | 0.005 |
| Abortus | 0.4 ± 1.0 | 0.1 ± 0.3 | 0.063 |
| Cerclage week | 22.2 ± 2.4 | 21.4 ± 2.8 | 0.344 |
| Birth week | 34.5 ± 5.0 | 33.4 ± 2.3 | 0.309 |
| Elapsed time (week) | 12.4 ± 5.2 | 12.0 ± 2.9 | 0.762 |
| Cerclage EFW mean (g) | 493.5 ± 193.6 | 380.2 ± 152.3 | 0.053 |
| Birth EFW mean (g) | 2499.7 ± 1040.8 | 2101.5 ± 484.6 | 0.025 |
| Cervical dilatation | |||
| Yes (%) | 26 (72.3) | 5 (38.5) | 0.007** |
| No (%) | 10 (27.7) | 8 (61.5) | |
| PPROM | |||
| Yes (%) | 7 (19.4) | 3 (23.1) | 0.781** |
| No (%) | 29 (81.6) | 10 (76.9) |
*Student t-test.
**Χ2 analysis was applied.
PPROM: premature preterm early rupture of membranes; SD: standard deviation; EFW: estimated fetal weight; g: grams.
A comprehensive analysis of all cases revealed that the earliest cerclage procedure was conducted at 16 gestational weeks, whereas the latest was performed at 27 weeks (mean: 21.7 ± 2.3 weeks; minimum: 16 weeks; and maximum: 27 weeks). In the present study, three patients underwent cerclage between 24 and 27 weeks of gestation. Of these, three were singleton pregnancies, and cerclage was performed subsequent to the detection of cervical patency. All three cases reached the full term after the cerclage procedure was performed. A total of 62 fetuses were evaluated for perinatal outcomes, as detailed in table 3.
Table 3 Patients neonatal results
| Perinatal outcomes, n (%) | Media ± SD |
|---|---|
| NICU | |
| Yes, n (%) | 27 (43.5) |
| No, n (%) | 35 (56.5) |
| Mortality | |
| Yes, n (%) | 3 (4.8) |
| No, n (%) | 59 (95.2) |
| APGAR 1 min | 5.4 ± 1.8 |
| APGAR 5 min | 7.3 ± 1.9 |
| Hospitalization duration (days) | 13.6 ± 16.5 |
n: number of cases, SD: standard deviation; NICU: newborn intensive care unit; min: minute.
Among the fetuses (n = 3, 4.8%) were lost as postnatal exitus, and there was no intrauterine exitus. The rate of neonatal intensive care unit (NICU) hospitalization requirement was (n = 27, 43.5%). All of these hospitalizations were due to prematurity and newborn transient tachypnea. The mean length of stay in the new NICU unit in the neonatal period was calculated as 13.6 ± 16.5 days.
Discussion
In our study, an emergency cerclage procedure was performed in a total of 49 patients with singleton and twin pregnancies with cervical shortness or cervical dehiscence. Similar results were found in both singleton and twin pregnancies that underwent emergency cerclage, and the results showed that the emergency cerclage procedure can be recommended up to the 27th gestational week in pregnancies threatened by cerclage failure.
Detection of a short cervix or cervical dilatation in the second trimester of pregnancy may be a sign of miscarriage or preterm labor. Cervical cerclage is known to be effective in patients with a history of premature birth and a short cervix12. Emergency cervical cerclage is recommended in patients with clinically detected cervical patency in the second trimester, but labor has not started, and there is no evidence of infection or bleeding13,14. Consequently, CL measurement during the second trimester of pregnancy is a crucial and readily achievable procedure for all pregnant women. By measuring the length of the cervix, it is possible to implement treatment strategies that may prolong the gestation period in pregnancies with a high risk of PTD.
The present study demonstrates that emergency cerclage in patients with cervical shortness and cervical dilatation can be an effective method for prolonging the gestation period. Furthermore, comparable success rates in singleton and twin pregnancies suggest that cerclage may also be a viable option for multiple pregnancies.
Ultrasonographic changes are detected before cervical changes are detected by examination. In most pregnant patients with CL 10-25 mm by TVU in the second trimester, the cervix feels long and closed on physical examination. Cervical effacement and dilatation are usually not detected until CL ≤ 10 mm by TVU. In one study, only one-third of patients with CL < 11 mm had cervical dilatation ≥ 1 cm on physical examination15. All these data emphasize the importance of second-trimester CL measurement.
Some conditions need to be specifically ruled out in patients with cervical shortening or dilatation. The first condition to be ruled out is active labor and vaginal infections. First of all, risk factors should be eliminated with intensive follow-up of these pregnant women16. Normal cervical ripening occurs over days to weeks, whereas cervical change in labor occurs over minutes to hours. A short or dilated cervix may be the first clinical sign of impending preterm labor triggered by subclinical inflammation17. A history of placental abruption or bleeding from placenta previa should be excluded through physical examination and ultrasound imaging. These conditions have the potential to cause biochemically mediated cervical ripening, which may result in second-trimester pregnancy loss or extremely PTD18. Infections that may cause PTD should be excluded through the implementation of appropriate diagnostic procedures, including transabdominal amniocentesis, urine culture, and complete urinalysis. In a study, the incidence of intraamniotic infection resulting from amniocentesis was found to be approximately 20-50% in patients with a dilated cervix of ≥ 2 cm on routine digital or speculum examination19. In the present study, cerclage was performed in all cases after the exclusion of infection according to the results of laboratory tests and the absence of infection according to the results of physical examinations.
The management of patients diagnosed with CI is still controversial. Different opinions have been reported regarding progesterone treatment, which is one of the treatments for CI. In a study comparing emergency cerclage and bed rest for CI, emergency cerclage was shown to significantly increase mean gestational age and perinatal survival in both singleton and twin pregnancies20,21. In another study, overall survival after emergency cervical cerclage was 74%, fetal survival 88%, and neonatal survival 90%. Singleton and twin pregnancies showed similar survival and prolonged the gestation period by 52 and 37 days, respectively21. In our study, the mean time to delivery was 12.4 ± 5.2 weeks in patients who underwent cerclage in singleton pregnancies with USG indication and clinical indication in the second trimester and 12.0 ± 2.9 weeks in patients who underwent cerclage in twin pregnancies. In addition, fetal survival was 100%, and neonatal survival was 95.2% in our study. We found that emergency cerclage had a favorable effect on pregnancy and neonatal outcomes in both singleton and twin pregnancies. We think that this may be related to the exclusion of other causes of cervical shortness with perioperative examinations of the patients before cerclage, as well as anti-inflammatory and antibiotic treatment.
A study was conducted on patients with intra-amniotic infection/inflammation, as detected by amniocentesis, who were treated with antibiotics (ceftriaxone, clarithromycin, and metronidazole). The results demonstrated that approximately 60% of patients exhibited successful treatment outcomes following the regression of the intra-amniotic inflammatory process or infection. Furthermore, 75% of patients exhibited complete resolution of the infection or inflammation11. In our study, all patients with cervical dilatation but prolapsed amniotic membranes or with cervical shortness but no dilatation who had evidence of inflammation on USG findings were started on antibiotherapy, similar to the literature. The lack of amniotic fluid sampling to prove intra-amniotic infection/inflammation is one of the limitations of our study.
Rupture of membranes during the cerclage procedure or in the immediate post-operative period is uncommon in history-based cerclage but is of concern in emergency cerclage. In the absence of perioperative rupture, the risk of PPROM at < 34 gestational weeks may not differ according to the indication for cerclage22. In our study, the PPROM (< 32 weeks) complication rate was 25.8% in the cerclage group and 11.1% in the USG indication group according to clinical indication, and no statistically significant difference was observed.
The majority of clinicians avoid performing cerclage after 24 weeks of gestation due to the fact that the majority of data on the efficacy of this procedure are derived from pregnancies that are < 24 weeks in duration. In addition, there is a potential risk of rupture of the fetal membranes, which could result in premature delivery of the baby. Both the SMFM and the International Society of Ultrasound in Obstetrics and Gynecology recommend emergency cerclage in singleton pregnancies with no previous history of spontaneous PTD but with a very short CL (≤ 10 mm) before 24 weeks23,24. The findings of our study indicate that emergency cerclage performed by experienced specialists until the 27th week of gestation has a similar effect on prolonging the gestation period. Similarly, the efficacy of cerclage in twin pregnancies remains a topic of debate. However, the findings of our study indicate that cerclage is as effective in twin pregnancies with a short or dilated cervix as in singleton pregnancies. The prospective design of our study, the inclusion of both singleton and twin pregnancies, and the comparison of patients with cervical shortness and cervical dilatation within a single study represent the studys key strengths.
It should be noted that our study is subject to a number of limitations. The present study is limited by its single-center design, the relatively small number of patients included, the absence of a control group, and the exclusion of intraamniotic infection.
Conclusions
In both singleton and twin pregnancies, emergency cerclage between 16 and 27 weeks of gestation in patients with cervical shortening or dehiscence has been demonstrated to prolong the gestation period under appropriate conditions by experienced specialists. Nevertheless, each case should be considered on an individual basis, and the potential risks associated with the procedure should be carefully evaluated.

